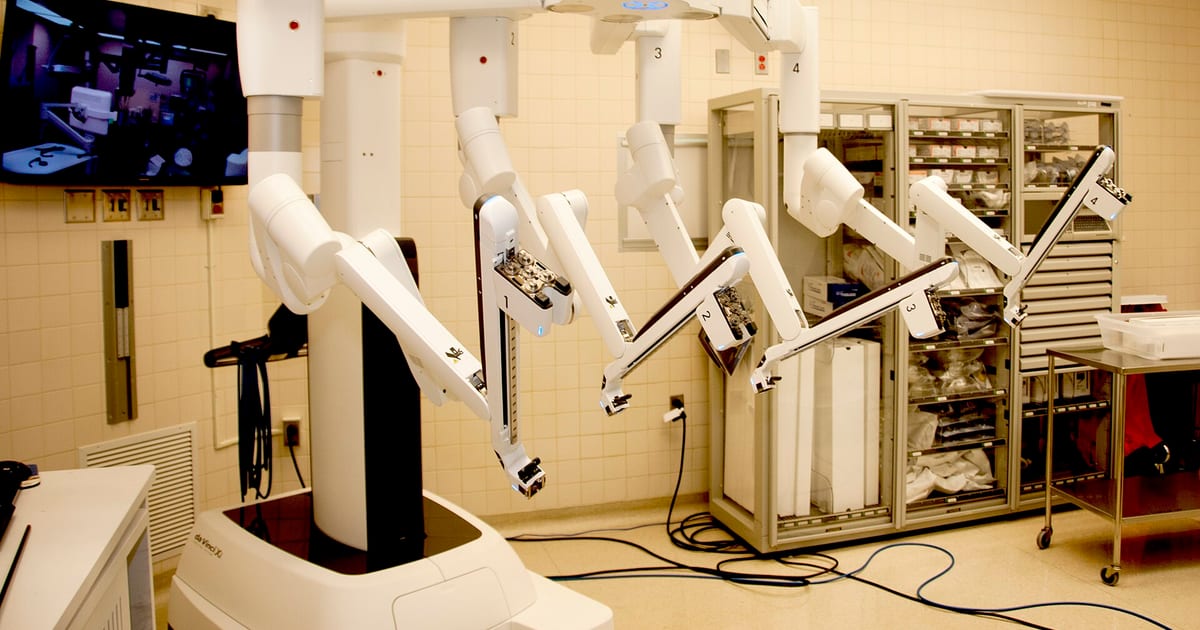
Will AI Replace Doctors? What 2026 Benchmarks Show
Summary & Key Takeaway
AI will replace tasks, not doctors. It already drafts notes, reads images, flags risk, and answers patient questions. It does not examine a patient, perform a procedure, carry legal responsibility, or manage a decade of changing symptoms. The benchmark evidence is strong enough to take seriously and too narrow to justify the headline that doctors are obsolete.
◆ Core Insights
- MedQA scores have risen above 90%, but MedQA is a four-option exam that supplies the question, the options, and the answer format.
- The strongest real-world study, AMIE, reached 59.1% top-1 accuracy versus 33.6% for primary care physicians in a simulated OSCE.
- AI is already replacing tasks in documentation, imaging second reads, triage, coding, and patient education.
- Replacement of doctors would require prospective trials, regulatory approval, liability reform, and integration into care, none of which exists at scale.
- The realistic future is fewer administrative tasks per doctor and more time for judgment, procedures, and relationships.
Try it yourself — free
Experience the medical AI that powers this article. Ask questions, check symptoms, or analyze lab results.
Want to know what a tool does with a panel like yours? See how the lab interpreter reads a blood panel.
Related Lab Tests
The short answer
AI is replacing tasks at a steady pace and doctors at a much slower one. The tasks are document drafting, image triage, coding, prior authorization, and first-pass patient questions. The doctor's job also includes the physical exam, procedures, uncertainty, accountability, and the relationship that makes a difficult conversation possible.
That is not a promise that nothing will change. It is a statement about where the evidence is. A model that can score 91% on a medical exam is impressive. It is not the same as a system that can run a clinic, and the gap is not a small engineering detail.
The clearest way to see the gap is to compare the two jobs directly. A benchmark asks a question and supplies the options. A clinic asks the patient to describe a problem, decides which question matters next, examines the body, orders a test, interprets the result in context, and takes responsibility for the plan. Our AI doctor vs real doctor comparison walks through each of those steps and shows where the evidence actually supports automation.
What the benchmarks actually measure
Each benchmark answers a different question. MedQA measures multiple-choice exam accuracy. PubMedQA measures reasoning over research abstracts. HealthBench measures the quality of a health conversation against physician-written rubrics. A simulated OSCE measures diagnostic conversation under controlled conditions. None of them measures whether a patient gets better.
| Benchmark | What it measures | What it misses |
|---|---|---|
| MedQA | Four-option USMLE-style exam accuracy | Conversation, exam, longitudinal context, accountability |
| PubMedQA | Reasoning over research abstracts | Real patients, time pressure, competing risks |
| HealthBench | Conversation quality against physician rubrics | Clinical outcomes and system-level safety |
| Simulated OSCE | Diagnostic conversation with trained actors | Live care, procedures, follow-up, liability |
| Prospective clinical trials | Outcomes in real care | Rarely run for general chatbots |
Why benchmark scores keep rising
Scores rise for good reasons and bad ones. Good reasons include better reasoning, retrieval, and medical tuning. Bad reasons include training on the test, evaluating with a forgiving prompt, and reporting the best of several attempts. A leaderboard that does not control for those choices rewards optimization, not necessarily safety.
The result is a treadmill. Each new model reports a higher number, and each number is less informative than the last because the evaluation is saturated. MedQA was designed to be hard for 2021 models. When models exceed 90%, the exam stops discriminating between good and excellent clinical reasoning.
That is why the field is moving toward conversation-based and outcome-based evaluation. HealthBench and simulated OSCE studies are harder to game because they require a sequence of decisions. They are also harder to run, which is why there are fewer of them. Our AI doctor accuracy guide tracks the shift and explains which numbers are worth trusting.
The strongest real-world result so far
AMIE, published in Nature in 2025, is the most cited attempt to move beyond multiple-choice questions. In a simulated OSCE, the system reached 59.1% top-1 diagnostic accuracy, compared with 33.6% for primary care physicians. It also scored well on communication and management reasoning.
The result is significant because it tests a conversation, not a vignette. The system had to ask questions, narrow a differential, and explain a plan. That is closer to clinical work than MedQA and a real advance.
The limits are equally important. The patients were actors, the interaction was text-only, and the physicians knew they were in a simulation. Live care adds time pressure, interruptions, incomplete records, and consequences. A simulated OSCE is a bridge, not the destination.
Even so, the direction is clear. The more the evaluation looks like a conversation, the more the model has to demonstrate the skills that matter: asking, narrowing, explaining, and escalating. That is a better predictor of clinical usefulness than a multiple-choice score, even if it is still not proof of better outcomes.
Where AI already replaces tasks
The task replacement is real and underreported because it is unglamorous. Ambient documentation turns a conversation into a draft note. Imaging tools prioritize studies and flag likely findings for a radiologist to confirm. Risk models flag deteriorating patients. Coding tools suggest billing codes. Patient-education tools answer routine questions.
Each of these removes minutes or hours of work without removing the clinician from the decision. The cumulative effect is large: less time on the keyboard, more time on the patient. That is the version of AI in medicine that is actually shipping.
The pattern is consistent across industries. Automation absorbs tasks first, then roles, and only later, if ever, whole jobs. Medicine has a high barrier to the later stages because the cost of error is borne by a person and a license.
The tasks being automated are also the least satisfying parts of the job. Documentation, coding, prior authorization, and inbox management are administrative overhead. Removing them does not remove the doctor; it gives the doctor back the time that made the job worth doing. Our medical AI statistics overview collects the adoption numbers behind that shift.
The pattern also explains why the replacement headlines feel both plausible and premature. The tools are visibly good at the tasks people see, such as answering a question or summarizing a report. The tasks that protect the profession, such as examining a patient or managing a complication, are invisible until something goes wrong. A demo shows the visible part.
Why doctors are not replaced
First, the physical exam. A model cannot palpate an abdomen, listen to a murmur, or see that a patient is confused. Those observations change the probability of disease before any test is ordered. Second, procedures. Someone has to put in the line, set the fracture, and manage the complication.
Third, accountability. A clinician can be sued, disciplined, and required to explain a decision. A model cannot carry that responsibility, and someone has to own the output. Fourth, context. A patient's history, values, and social situation determine the plan as much as the diagnosis.
Fifth, trust. Patients bring fear and uncertainty, and a conversation with a person is part of the treatment. Sixth, the long tail. Rare disease, atypical presentations, and multi-system illness are exactly where models are weakest and clinicians are most valuable.
There is also a training pipeline problem. Someone has to teach the next generation of doctors to examine, decide, and take responsibility. If trainees spend their time supervising a model instead of practicing those skills, the profession loses the judgment it needs when the model fails. That is a slower risk than a headline-grabbing error, but it is a real one.
None of this means doctors should ignore the tools. It means the tools should be designed to keep the clinician in the loop for the parts that require judgment, and that the training system should protect the skills that cannot be learned from a screen.
Specialty-by-specialty outlook
The exposure is uneven. Radiology and pathology are image-heavy and high-volume, so they will see more task automation, but the radiologist's role in protocoling, quality, and complex cases remains. Primary care is broad and relational, which protects it, even as documentation and triage are automated.
The table is a map of tasks, not a forecast of layoffs. A specialty can lose half of its routine volume and still need the same number of clinicians, because the remaining cases are harder and take longer. The bottleneck in medicine is rarely the number of images; it is the number of decisions that require a person.
| Specialty | Most exposed tasks | Most protected tasks |
|---|---|---|
| Radiology | Image triage, measurement, draft reports | Protocoling, complex cases, procedures, communication |
| Pathology | Screening, quantification, draft reports | Diagnosis of ambiguous cases, molecular integration |
| Dermatology | Lesion triage and photo screening | Full-body exam, procedures, treatment decisions |
| Primary care | Documentation, routine questions, coding | History, exam, prevention, chronic care, relationships |
| Surgery | Planning, imaging review, documentation | The operation, complications, judgment under pressure |
| Psychiatry | Screening, notes, psychoeducation | Risk assessment, therapy, medication management |
| Emergency medicine | Triage support, documentation, imaging flags | Resuscitation, procedures, disposition under uncertainty |
The three scenarios that actually matter
The first scenario is augmentation. AI drafts the note, flags the image, and answers the routine message while the clinician handles the judgment. This is the most likely near-term outcome, and it is already happening in systems that have invested in integration.
The second scenario is substitution at the margins. A patient with a minor, well-defined problem uses an AI first and sees a clinician only if the tool escalates. This works for some urgent-care and triage use cases, but it shifts risk to the patient and requires a clear escalation path. It is plausible in high-volume, low-acuity settings, not in complex care.
The third scenario is autonomous diagnosis. This would require prospective trials, regulatory approval, liability reform, and patient acceptance. It is the scenario in the headlines and the least supported by current evidence. The distance between the first scenario and the third is the distance between a tool that helps a doctor and a system that replaces one.
What would have to be true for replacement
Replacement would require prospective trials showing better outcomes in real care, not retrospective accuracy on a benchmark. It would require regulatory approval for autonomous action, a liability framework that assigns responsibility when a model is wrong, and integration into electronic records and workflows.
It would also require patient acceptance. People want convenience, but they also want a person when they are scared. A system that is faster and cheaper but feels abandoned will not replace the relationship, even if it matches the diagnosis.
None of these conditions is close to being met at scale. The realistic path is augmentation: AI handles the volume, the clinician handles the judgment and the human parts.
The liability question is the hardest. If a model recommends a test and the clinician follows it, who is responsible when the diagnosis is wrong? The clinician signed the order, but the model shaped the decision. Current law has no clean answer, and until it does, autonomous diagnosis will remain limited to narrow, cleared tasks. Our AI doctor safety guide covers the regulatory and liability landscape in more detail.
What patients should do now
Use AI to prepare, not to decide. Bring a written timeline, a medication list, and a list of questions. Ask the model to explain the reasoning and cite sources. Then take that preparation to a clinician who can examine you and order the right test.
Do not use a chatbot for an emergency. Do not assume a high benchmark score means the tool is safe for your case. Do not upload a report you do not need to share. Those three rules prevent most of the harm.
It also helps to separate the tool's confidence from its competence. A model can write a fluent paragraph about a diagnosis it has never seen in a real patient. Fluency is not evidence. Ask for the source, the uncertainty, and the next step, and treat the absence of those as a warning.
The doctors who thrive will be the ones who use these tools well. The patients who benefit will be the ones who use them as a bridge to care, not a replacement for it.
That is also why the specialty question is less dramatic than it sounds. Radiology will not lose its radiologists; it will lose some of the routine reads. Primary care will not lose its doctors; it will lose some of the inbox. The headline asks whether AI will replace doctors. The evidence asks which tasks each doctor wants to keep. For a specialty-by-specialty view, see our analysis of the first specialty AI is replacing, and for the exam-score side of the story, our review of the doctor who passed fewer exams.
Ready to try Premedice?
Get instant, AI-powered explanations of your lab results and symptoms — powered by 45+ clinical sources.
Continue Reading



Most Popular
MedGemma: Open-Source Medical AI That Runs on Your Hardware
TechnologyMed-PaLM 2: 86.5% MedQA Score, Zero Doctors Using It (2026)
ResearchWhich Medical AI Can You Actually Trust With Your Bloodwork?
ResearchGoogle's MedGemma Is Free - But Should You Use It on Patients?
TechnologyMed-PaLM 2: 86.5% on MedQA — Why Doctors Won't Use It (2026)
ResearchDr. Elena Rostova, MD, PhD
Dr. Rostova is a clinical informatics specialist with 14 years of research in machine-learning systems for diagnostic decision support at Stanford Medical Center.
Expert Takeaway
The specialties most exposed are those built on high-volume, image-based pattern recognition. The specialties most protected are those built on procedures, physical examination, longitudinal relationships, and accountability. Most doctors will work with AI rather than be replaced by it.
Browse by Topic
QFrequently Asked Questions
Q1Will AI replace doctors?
AI will replace tasks, not doctors. It already drafts notes, reads images, and answers routine questions. It does not examine patients, perform procedures, carry legal responsibility, or manage long-term relationships, and those are core parts of the job.
Q2Will AI replace radiologists?
Radiologists will see more task automation in image triage and draft reporting, but their role in protocoling, complex cases, procedures, and communication remains. The realistic outcome is fewer routine reads per radiologist, not zero radiologists.
Q3What did the AMIE study show?
AMIE reached 59.1% top-1 diagnostic accuracy in a simulated OSCE, compared with 33.6% for primary care physicians. The study used trained actors and text-only interaction, so it is a strong simulation result, not proof of live clinical superiority.
Q4Do AI models score higher than doctors on medical exams?
Yes, on some exams. Med-Gemini scored 91.1% on MedQA, and other models exceed 85%. Those exams are multiple-choice and supply the question and options, so they do not measure the full work of diagnosis.
Q5Which medical specialties are most at risk?
Specialties built on high-volume, image-based pattern recognition, such as radiology and pathology, face the most task automation. Specialties built on procedures, physical examination, and long-term relationships face less.
Q6Can AI diagnose better than a doctor?
On narrow image and signal tasks, AI can match or exceed specialist performance in controlled studies. On undifferentiated symptoms, multi-system disease, and rare conditions, it does not. The answer depends on the task and the study design.
Q7Will AI make healthcare cheaper?
It could reduce the cost of documentation, triage, and routine interpretation, but those savings are not guaranteed to reach patients. The bigger near-term effect is freeing clinician time, not lowering the total cost of care.
Q8Should I trust an AI doctor?
Trust it for explanation and preparation, not for diagnosis or emergencies. Look for citations, red-flag guidance, and a clear statement of limits. Verify important claims with a clinician and seek emergency care for urgent symptoms.
Verified References & Literature
What Disease Does This Patient Have? A Large-Scale Open Domain Question Answering Dataset from Medical Exams
Jin et al., arXiv, 2021
View SourceNew AAMC Report Shows Continuing Projected Physician Shortage
Association of American Medical Colleges, 2024
View SourceClinical Decision Support Software: Guidance for Industry and Food and Drug Administration Staff
U.S. Food and Drug Administration, 2022
View SourceEthics and Governance of Artificial Intelligence for Health
World Health Organization, 2021
View SourceGet a structured second read in seconds
Upload lab results, describe symptoms, or ask about a diagnosis — Premedice gives you medically-grounded answers backed by 30+ clinical databases.

